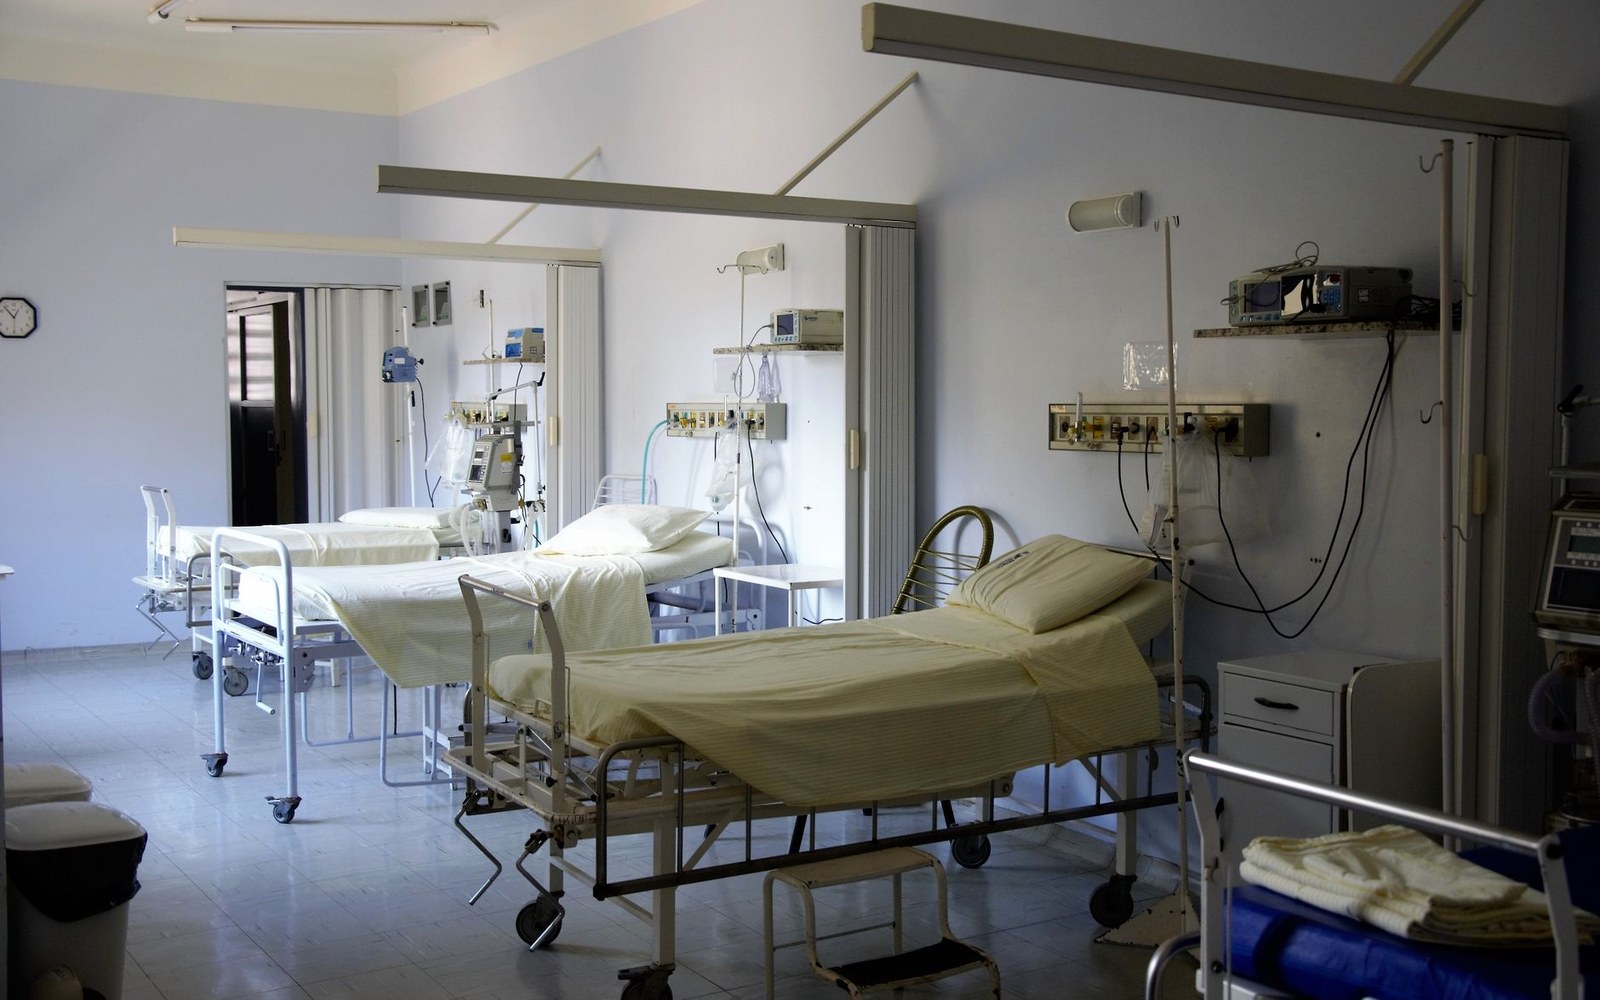
The number that lifted every ceiling in a Victorian hospital ward
Before germ theory settled the argument about how disease spread, the dominant belief was that foul air was the mechanism. Crowded wards smelled, patients sickened, and the causal chain seemed self-evident. The response was to dilute: give each patient enough air volume that whatever poisoned it would be too diffuse to harm. The result was a standard expressed not in square feet of floor or linear feet between beds, but in cubic feet — a three-dimensional ration. Volume became the measure of safety.
Florence Nightingale, whose Notes on Hospitals (1859) codified the Nightingale ward as a set of dimensional rules, was explicit about this. Her preferred figure was around 1,500 cubic feet per patient. The air was assumed to turn over — through open windows and roof ventilators — at a rate that kept the effective supply closer to what one person needed than to what the whole ward shared. The geometry followed: if you hold the bed count fixed and hold the floor area roughly constant, the only dimension left to vary is height. The standard pulled ceilings up.
The arithmetic in practice
Take a ward of thirty beds. At 1,500 cubic feet per bed, you need 45,000 cubic feet of air volume. If the ward is sixty feet long and twenty-five feet wide — the proportions Nightingale recommended — the floor plate gives you 1,500 square feet. To achieve 45,000 cubic feet, the ceiling must sit exactly thirty feet above the floor. That is not unusual for a Victorian hospital ward. It is the reason they feel more like naves than rooms.
The figure was not Nightingale's alone. The standard was circulating in British sanitary reform before her book, and it influenced the design briefs used by Poor Law guardians, metropolitan asylums and colonial hospitals alike. John Shaw Billings, who drew the plan for Johns Hopkins Hospital in Baltimore, worked from ventilation targets that were in the same order of magnitude. The goal was to engineer a building whose geometry guaranteed an air ration, on the assumption that mechanical ventilation was unreliable and human behaviour worse.

The standard also shaped what could not be saved. A ward that had to meet 1,500 cubic feet per bed while holding a given floor area could not reduce the section. When reformers tried to lower costs by cutting ceiling heights, sanitarians objected — correctly, within their own logic — that doing so was the equivalent of taking beds away from the ward while keeping the patients. The cubic-feet standard became a constraint that architects had to design around, not through.
After the standard
Germ theory erased the theoretical basis for the volume prescription. Once infection was understood to travel on specific organisms rather than in generalised bad air, the reason to engineer a precise quantity of air per patient dissolved. There was no bacteriological argument for a ceiling thirty feet high; bacteria survived perfectly well in tall rooms. The standard lingered in building codes for a generation — institutions are slow to unlearn their own reasoning — but it could no longer defend itself in principle, only in precedent.
What replaced it was flow rather than volume: air changes per hour, a mechanical standard that could be met in any ceiling height if the ductwork was sufficient. The sealed tower hospital of the mid-twentieth century compressed wards into deep plans with low ceilings and centralised air-handling plant, achieving a ventilation target that its engineers could specify to the decimal point, in a building whose geometry would have horrified every sanitary reformer who had ever measured a ward.
The Victorian ceiling survives in surviving Victorian hospitals as a spatial fact whose reason has been forgotten. Stand in one and you feel the logic before you can name it — all that height over a relatively narrow floor, windows on both walls, the sense that the room is working. It was. The number was 1,500.